





Is an Uneven Hairline Normal?
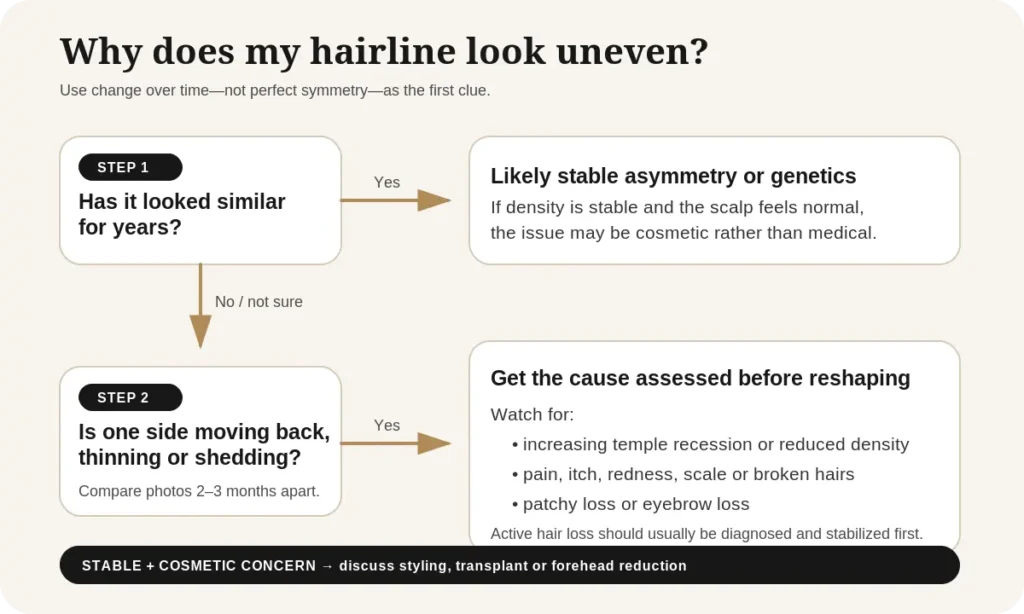
The most useful distinction is stable asymmetry versus progressive change. A stable hairline can be cosmetically uneven without being unhealthy. A hairline that is moving backward, becoming more see-through or developing new gaps deserves a closer look.
If you are unsure whether the issue is a naturally high hairline or actual recession, compare this guide with our article on mature hairline vs. receding hairline. If your concern is mainly forehead height rather than left-right symmetry, see what is considered a big forehead.
7 Common Causes of an Uneven Hairline
1. Natural asymmetry and genetics
Some people are simply born with one side of the frontal hairline higher than the other. The temples can also have different angles or density. This is especially likely when childhood or teenage photographs show the same pattern and there has been no obvious progression.
Natural asymmetry does not need treatment. If the shape bothers you aesthetically, the right option depends on whether the issue is the height of the whole forehead, a sparse corner, a widow’s peak, or a small contour difference.
2. Androgenetic alopecia (pattern hair loss)
Pattern hair loss can make an existing asymmetry more obvious. In men, recession often begins at the temples and can develop into an M-shaped hairline. The two sides do not always change at exactly the same pace, so one corner may look deeper first. In women, hereditary hair loss more commonly causes diffuse thinning, but frontal changes can still occur.
Look for change over time: deeper temple corners, finer hairs around the edge, reduced density behind the hairline, or thinning elsewhere on the scalp. The American Academy of Dermatology notes that a receding hairline can be an early sign of hereditary hair loss, while Cleveland Clinic describes temple recession and thinning as common features of male pattern hair loss.
3. Traction alopecia from tight hairstyles
Ponytails, braids, extensions, buns and other styles that repeatedly pull on the same areas can damage hairs along the frontal and temporal edge. If one side is under more tension because of how you part, tie or style your hair, the hairline can begin to look uneven.
The American Academy of Dermatology specifically warns that the hairline is one of the first places traction alopecia may become visible. Early changes may improve when the pulling stops; long-standing traction can lead to permanent loss.
4. Alopecia areata or localized patchy hair loss
Alopecia areata can create sudden, smooth patches of hair loss. If a patch touches the frontal hairline, the border can appear notched or uneven rather than forming a classic round bald spot. This pattern needs a medical diagnosis because the treatment approach is very different from cosmetic hairline reshaping.
5. Frontal fibrosing alopecia and other scarring conditions
Frontal fibrosing alopecia (FFA) is a scarring form of hair loss that can cause progressive recession along the front and temples. It is more common in women, particularly after menopause, but it can occur in other groups. Eyebrow thinning, a band of lighter or shiny skin, redness around follicles, itch, pain or scale can be clues.
Because scarring hair loss can permanently destroy follicles, early dermatologic assessment matters. A 2025 review describes FFA as a progressive scarring alopecia characterized by frontal and temporoparietal recession, often with eyebrow involvement.
6. Breakage, scalp inflammation or damage near the edge
Not every “receding” corner is true follicle loss. Broken hairs from chemical processing, heat, friction or scratching can make the border look irregular. Inflammatory scalp conditions can also alter density around the hairline. The presence of scale, redness, tenderness, crusting or many short broken hairs is a reason to look beyond simple genetics.
7. Hair direction, cowlicks, haircuts and visual illusion
A barber line-up, very short haircut, cowlick or side part can expose small differences that were always present. Wet hair and overhead lighting can also make one temple appear thinner. Before assuming your hairline is changing, compare dry hair in the same lighting and from the same camera angle.
Uneven Hairline Causes: Quick Comparison
| Possible cause | Typical clues | Usually stable or progressive? | Best next step |
|---|---|---|---|
| Natural asymmetry | Present for years; similar density on both sides; no scalp symptoms | Usually stable | Monitor or consider cosmetic options only if desired |
| Pattern hair loss | Temple recession, finer hairs, reduced density, possible crown thinning | Often progressive | Hair-loss assessment before surgical redesign |
| Traction alopecia | History of tight styles; broken hairs or thinning at stressed edges | Can progress with continued tension | Reduce traction and seek assessment if loss persists |
| Alopecia areata | Smooth, localized patch or sudden notch in the hairline | Variable | Dermatology assessment |
| Frontal fibrosing/scarring alopecia | Receding band, eyebrow loss, redness, scale, itch or shiny skin | Can be progressive and permanent | Prompt dermatology assessment |
| Breakage/inflammation | Short broken hairs, irritation, scale or recent chemical/heat damage | Depends on cause | Address the underlying scalp or hair-shaft problem |
| Haircut/cowlick/lighting | Looks different with styling, wet hair or a fresh line-up | Usually visual | Recheck with standardized photos |
Does an Uneven Hairline Mean You Are Balding?
Not by itself. Symmetry is a weak diagnostic clue; progression and density are stronger clues. An uneven hairline that has not changed for years is very different from a hairline that is visibly moving backward every few months.
To monitor it, take one front-facing photo and one 45-degree photo of each temple under the same lighting. Keep your hair dry and pulled away from the edge. Repeat every two to three months. Look for movement of the corners, a larger gap between the eyebrows and hairline, more visible scalp, or increasingly fine hairs at the border.
Signs that deserve faster assessment
- rapid or obvious change over a few months;
- patchy hair loss rather than gradual recession;
- itching, pain, burning, redness, scale or pustules;
- eyebrow loss or loss in other areas;
- a shiny scar-like band where follicle openings are disappearing.
How to Fix an Uneven Hairline
The right solution depends on the cause. Trying to “fix” an actively receding hairline with surgery before understanding the hair-loss pattern can create a result that becomes unbalanced as native hair continues to thin.
Stable, naturally uneven hairline
Options may include styling, camouflage, scalp micropigmentation, transplantation for small contour changes, or forehead reduction when the entire hairline is naturally high and stable.
Hairline that is actively changing
Identify the cause first. Medical management or removal of a trigger may be more important than immediately lowering or reshaping the hairline.
1. Styling and camouflage
For mild asymmetry, changing the part, adding a fringe, softening a sharp temple with longer face-framing hair, or avoiding very tight line-ups may be enough. Hair fibers and scalp micropigmentation can reduce contrast where the scalp shows through, but they do not change the position of the follicles.
2. Treat the underlying hair-loss process
If the asymmetry is caused by pattern hair loss, traction, inflammation or another medical condition, treatment should target that cause. A dermatologist may use scalp examination, trichoscopy, history and—when needed—additional tests to distinguish the possibilities. Medication choices vary by diagnosis, age, sex, pregnancy status and medical history, so they should be individualized.
3. Hair transplantation for localized contour correction
A hair transplant can be useful when the hairline is stable but one corner is sparse, a widow’s peak is too pronounced, or the frontal contour needs detailed redesign. It can also be considered after hair loss has been appropriately assessed and stabilized. Our guide to hair transplant procedures in Turkey explains the general approach.
If your main question is whether grafting or scalp advancement would make more sense, see forehead reduction vs. hair transplant.
4. Forehead reduction for a naturally high, stable hairline
Forehead reduction (hairline lowering surgery) physically advances the hair-bearing scalp and removes a strip of forehead skin. It is designed for a naturally high, stable hairline rather than untreated active recession. Some contour adjustment can be incorporated into the planned incision, but candidacy depends on scalp laxity, hair density, hair-loss risk and scar considerations.
Read the full forehead reduction surgery guide for candidacy, technique and recovery. If you want to explore non-surgical or less invasive ways to change the appearance of forehead height, see forehead reduction without surgery.
Uneven Hairline in Women vs. Men
In men, an uneven temple can overlap with early androgenetic alopecia, especially when the corner is getting deeper and hairs behind the line are becoming finer. The classic pattern may eventually become more obviously M-shaped.
In women, a naturally irregular frontal edge is common, but new recession deserves attention because female pattern hair loss often presents differently from the classic male pattern. Tight hairstyles can also affect the temples, and frontal fibrosing alopecia is an important diagnosis to exclude when recession is accompanied by eyebrow loss, itching, redness or a smooth scar-like band.
The practical rule is the same for both sexes: stable shape is usually less concerning than visible change.
When Should You See a Doctor About an Uneven Hairline?
Consider a professional hair-loss assessment if you can document progression, if one side is thinning rather than simply sitting higher, or if the scalp is symptomatic. Earlier evaluation is particularly important for scarring hair loss because lost follicles may not regrow.
If your hairline is stable and the concern is purely aesthetic, a consultation can instead focus on proportions, donor density, scalp laxity and the trade-offs between hair transplantation and forehead reduction.